Exploring the nutritional delivery space in recognition of Feeding Tube Awareness Week in February.
By Jenna Hughes

Proper nutrition plays a critical role in patients’ wellness, healing and recovery. Those receiving care in post-acute, long-term and at-home facilities may require nutrition via a feeding tube if unable to consume food orally.
Consequently, it is becoming increasingly important that post-acute hospital and healthcare facility staff and caregivers are trained on the innovative solutions in nutritional delivery to support adult and pediatric enteral feeding needs from the hospital to the home.
Feeding Tube Awareness Week is recognized this year during the week of February 8 through the 14 by the Oley Foundation, an organization enriching the lives of those living with tube feeding, to normalize the reality of receiving nutrition in different ways and to provide support for patients who rely on feeding tubes.
Enteral feeding and nutrition
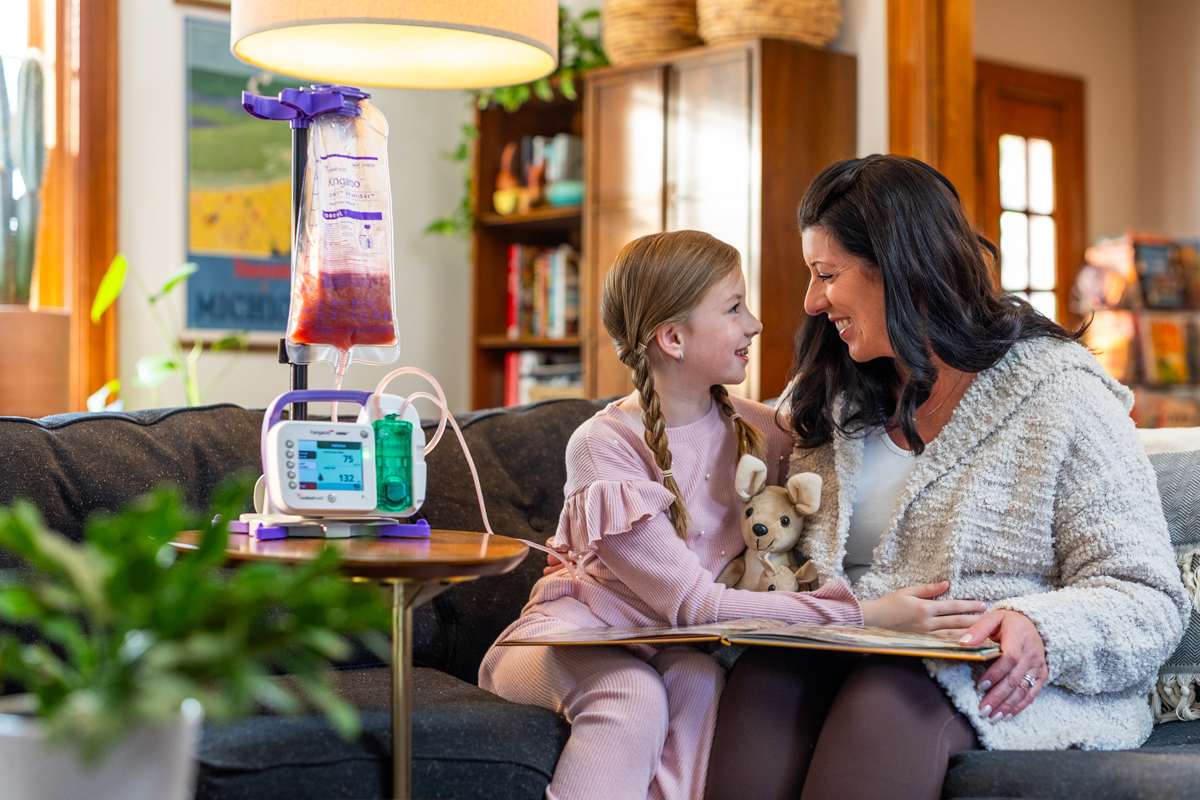
Advancements in clinical nutrition delivery have transformed care by enhancing patient diets, streamlining clinical workflows and leveraging new automated technology.
“Enteral feeding, also referred to as ‘tube feeding,’ is a way of providing nutrition directly into the gastrointestinal (GI) tract through an access device, or a feeding tube,” said Emily Miller, BSN, RN, medical advisor for nutritional delivery, Cardinal Health. Miller spent 11 years as a hospital bedside nurse, working directly with patients receiving enteral nutrition.
Enteral feeding is designed for patients who are physically unable to eat and swallow (dysphagia) or for those unable to obtain sufficient nutrition through eating and swallowing.
“Enteral nutrition can either be delivered through a short-term device that is placed through the nose or a long-term device that is surgically implanted into the stomach or small intestine,” said Miller.
Patients of all ages from infants to adults may have a feeding tube while in acute, post-acute and long-term care settings, and patients can live on a feeding tube for as long as needed.
“Related conditions include, but are not limited to cancer, critical illness, GI disease, or non-GI diseases such as stroke, kidney disease or lung disease,” said Miller.
Infants may also require enteral feeding if they cannot sufficiently suck or swallow during bottle or breast feeding, said Miller. This can happen if a baby is born prematurely or lacks the strength or skills to feed orally.
Sometimes, tube feeding is used for a short time, then decreased or stopped when the patient begins to eat enough by mouth, according to the Oley Foundation. Other patients receive tube feeding in long-term facilities or via at-home care their entire lives.
Advancements in enteral nutrition
In general, enteral nutrition can be administered by three different methods: manually with a syringe, using a gravity bag or via an enteral feeding pump.
“Gravity bags, typically hung above the patient on an IV pole or hook, provide enteral feeds using gravity without an electronic pump,” said Miller. “Both syringe and gravity feeds deliver food relatively fast, which can cause intolerance symptoms like nausea or vomiting in certain patients.”
Enteral feeding pumps, on the other hand, provide a portable nutrition option delivered at a controlled flow rate with the use of electronics, providing a customized and fully automated feeding experience, said Miller.
Despite the need for a medical prescription for enteral feeding to ensure adequate nutrition, some patients in both hospital and at-home settings remain at risk for malnutrition due to feeding intolerance and delivery challenges.
“Feeding intolerance can result from several factors, including poor gastroenteric access (from issues such as incorrect tube size or placement), partial bowel obstructions, medication side effects, hyperglycemia and electrolyte imbalances,” said Miller. “These issues can prevent patients from receiving the full volume of prescribed nutrition, leading to inadequate caloric intake and poor weight gain.”
Another significant contributor to feeding intolerance, said Miller, is the potential intolerance to standard commercial formulas.
Adult patients have traditionally been fed largely on commercially manufactured and ready-to-feed formulas. These can be liquids or powdered, concentrated formulas that are mixed with water. Some patients have demonstrated a lower tolerance for these standard, ready-to-feed formulas. This may result in gastrointestinal symptoms and reduced adherence to feeding.
Increasingly, patients receiving nutrition at home are shifting toward blenderized whole-food options to avoid these common feeding challenges. The term blenderized tube feeds (BTFs) refers to commercially available products and homemade blends made from real food ingredients, blended into a consistency that can be fed through a feeding tube, according to the Oley Foundation.
“Prepared or homemade blenderized foods differ from traditional, ready-to-feed formulas in that they are comprised of real, whole foods that are blended to a smooth consistency so they can be delivered through an enteral access device or feeding tube,” said Miller.
Most patients will also need water periodically delivered through the tube, called a “flush,” as the formulas do not provide enough water for their needs. Enteral feeding pumps that automatically feed and flush, like the Cardinal Health Kangaroo OMNITM Enteral Feeding Pump, can help promote hydration.
“With automatic flushing, this also helps reduce the burden on caregivers compared to manual flushing,” said Miller.
Organic, whole-food diets
According to Miller, one of the most significant changes in enteral nutrition is the shift toward whole-food, prepared blenderized diets – also referred to as BTFs. These types of diets are becoming increasingly popular. A recent global study indicated as many as 40% to 55% of adult patients receiving home enteral nutrition used BTF, she said.
“Studies have shown that when patients receive real-food blenderized tube feedings, they tend to experience fewer GI symptoms, ultimately lowering the risk of malnutrition,” said Miller. “Transitioning to BTFs has also been linked to higher patient and caregiver satisfaction, as well as relief from certain persistent GI symptoms that can occur with traditional, standard commercial formulas.”
These blends can retain more of the natural components of food including pulp and skins, which can make them thicker than standard commercial formulas, said Miller.
The International Dysphagia Diet Standardization Initiative (IDDSI) standardizes naming and descriptions for texture-modified foods and thickened liquids for people with dysphagia.
The IDDSI Framework, supported by the American Society for Parenteral and Enteral Nutrition (ASPEN), consists of a continuum of eight levels designating thickness, ranging from thin liquids to regular foods.
“Because BTF retains the integrity of real food including fiber and complex carbohydrates, it naturally falls into the thicker range of liquids on the IDDSI framework. This higher viscosity is one of the reasons specialized feeding sets and pumps are essential for delivering blenderized diets safely and accurately,” said Miller. “The Cardinal Health Kangaroo OMNITM Enteral Feeding Pump is the first attitude-independent feeding pump in the U.S. designed to deliver thick formula*.”
Standard feeding pumps and sets are not typically designed to handle thick formulas, which can lead to under-delivery of up to 22.5% of food compared to programmed volumes. This discrepancy can significantly impact nutritional status, especially in medically complex patients.
Personalized nourishment
BTF not only provides an alternative to standard formulas but also has the potential to improve the patient experience through personalized nutrition and natural nourishment.
“BTF allows patients and caregivers to incorporate familiar foods and individualized nutrition into enteral feeding, creating a more natural and inclusive experience,” said Miller. “It is also reported that BTF allows the patient to feel more included in family meals and social gatherings – ultimately improving quality of life.”
New commercially prepared BTF formulas are also increasingly becoming available, made with whole food-based ingredients and limited processing, said Miller.
“According to the Oley Foundation, when starting on BTF, it is best to start slowly and transition over a few days. Additionally, the Foundation recommends patients work with a healthcare provider and a registered dietitian/nutritionist to ensure that a diet is appropriate for the individual’s specific nutrition needs,” said Miller. “A nutritionist can evaluate food and fluid choices and monitor a person’s nutritional progress.”
BTF and commercial feeding products can be combined, according to the Oley Foundation. Caregivers can learn to prepare BTF at home by working with a registered nutritionist. When blending formula, it is best to use a high-powered blender and strain any bits and pieces that may clog a tube. Anyone who prepares BTF for a patient at home should be sure to practice proper food safety habits.
In both long-term care and at-home settings, nutritionists supporting enteral feeding should work closely with clinical care staff to ensure timely and appropriate enteral nutrition – while supporting this essential component of patient-centered, quality care.
“By enabling safe delivery of thick, whole-food blends, enteral feeding is moving away from a one-size-fits-all model toward an approach that offers patients a choice in enteral formula selection,” said Miller.
Notes:
* Thick formula can be defined as enteral fluids of smooth consistency that are categorized as Level 2, 3 or 4 Drinks within the International Dysphagia Diet Standardization Initiative (IDDSI) Framework.