Even as awareness grows, inconsistent adoption and limited federal guidance leave many facilities at risk. Distributor reps play a key role in helping sites implement effective smoke evacuation practices.
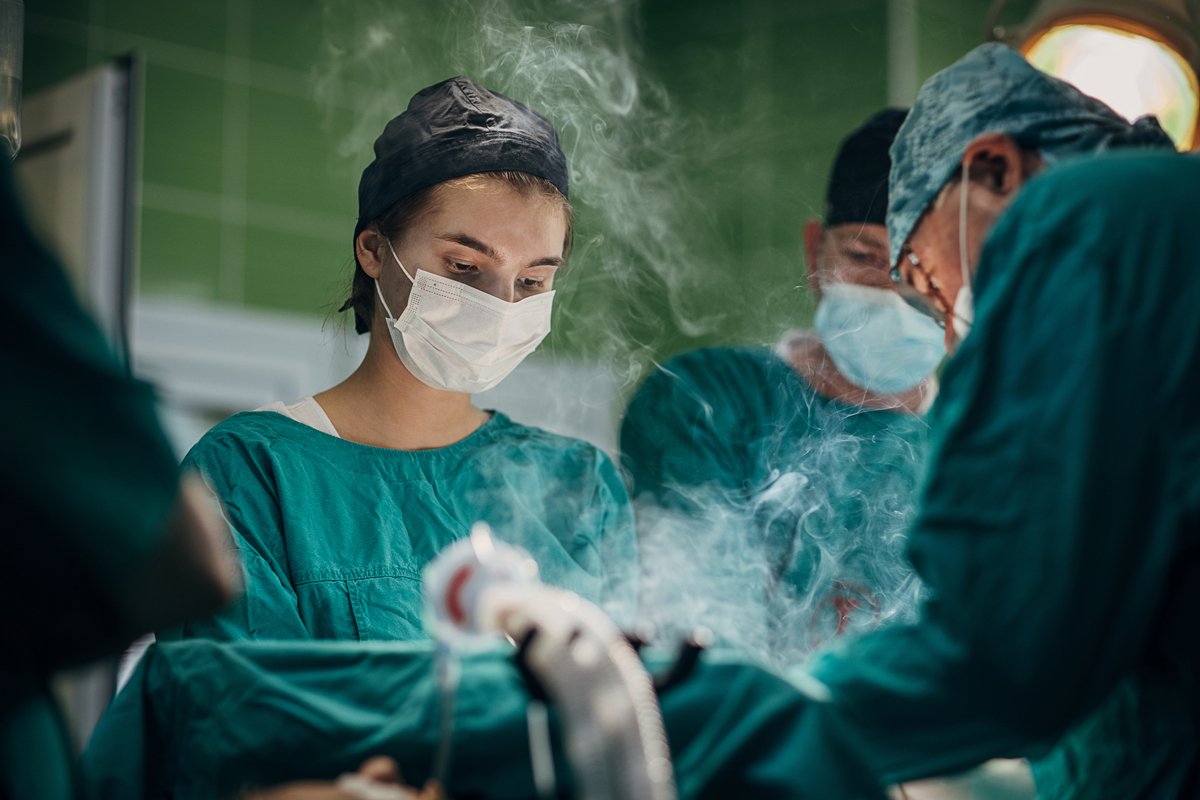
Distributors often encounter a common issue: while smoke hazards are recognized, safety measures aren’t standard in all situations where smoke is generated.
Federal regulation in the U.S. has not created a single universal requirement on smoke evacuation. The Occupational Safety and Health Administration (OSHA) has said it does not have a specific standard mandating surgical smoke evacuation, even as it highlights the hazard and points facilities to recognized controls. This has contributed to uneven adoption across sites of care; however, that is changing quickly at the state level and through accreditation expectations.1
While surgical smoke is often described as about 95% water vapor, the remaining fraction contains risk-driving components: ultrafine particles, volatile organic compounds, and other toxic gases/vapors (e.g., benzene, hydrogen cyanide, formaldehyde), and biological material (e.g., cellular debris, bacteria/viruses, and viral genetic material).2
Many people think that just having good room ventilation is enough to filter out contaminants, but it really isn’t effective at capturing pollutants where they come from.3 That’s why using local exhaust ventilation (LEV) systems is important.
Some think that “a little smoke doesn’t matter” or that smoke evacuation is only necessary for heavy smoke. However, OSHA states that any smoke should be evacuated. Smoke evacuators should be used whenever there are airborne particles and placed close to the source, ideally within 2 inches, to catch contaminants effectively.4
Lastly, surgical smoke should be treated like a regular workplace hazard that needs to be addressed with proper practices and training, whether it’s legally required.
How awareness has evolved over the past decade
Awareness has become a more recognized workplace hazard due to (a) stronger evidence, (b) formal guidance and accreditation, (c) clinician-led campaigns and (d) state legislation.
A key development in managing surgical smoke has been the increased awareness of national guidelines and accreditation efforts. The Joint Commission highlighted the risks associated with harmful gases and vapors.2
The Association of Perioperative Nurses’ 2021 guidelines stress the need to evacuate and filter smoke during procedures that produce it. They recommend positioning capture devices near the source for better efficiency, using specific filters when necessary and including compliance checks in quality improvement efforts.5
In the past 5 to 10 years, new laws have raised awareness about the necessity of smoke evacuation in operating rooms. According to AORN, 20 U.S. states have enacted laws mandating smoke evacuation, with more laws being proposed. As a result, many healthcare facilities must now implement smoke evacuation practices.6
The focus on airborne contaminants during COVID-19 has also led to greater acceptance of filtration and evacuation methods in surgery. Surgical professional organizations, such as the AORN, have been exploring ways to reduce exposure to surgical smoke.7
Safety facts distributor reps should know
Distributor reps can effectively collaborate with customers when they turn smoke evacuation education into clear, data-backed, and practical applications.
Surgical smoke contains toxic gases/vapors (e.g., benzene, hydrogen cyanide, formaldehyde), bioaerosols, dead/live cellular material, and viruses.
Surgical smoke can have a significant number of nanoparticles and ultrafine particles. These small particles can deeply enter the lungs when inhaled. Exposure to ultrafine particles is associated with irritation symptoms and can also impede a surgeon’s visibility.1
Smoke evacuation can be controlled with repeated practices: evacuate smoke, keep the evacuator activated whenever smoke is produced, and position the inlet close to the source (commonly within 2 inches) for effective capture. These are stated in OSHA and NIOSH guidance materials.4
Surgical masks can help protect against smoke, but they aren’t made to block tiny particles that can get into the lungs. Their ability to filter harmful substances varies significantly.5
“Portable smoke evacuation systems can reduce surgical smoke more than 99% under optimal conditions,” Aspen Surgical said. “The Bovie Smoke Shark 4-stage ULPA filter is 99.999% efficient in trapping .1-.2 μm particulates and microorganisms.”8
This highlights that using these systems can be effective, helping facilities decide which solutions are appropriate for their facility.”
AORN provides advocacy and education materials that highlight two key facts about surgical smoke: (a) it can contain over 150 harmful chemicals, and (b) the daily exposure for an OR team is equivalent to inhaling smoke from 27-30 unfiltered cigarettes. Follow up with a practical recommendation: always evacuate smoke at the source during any procedure that generates it.6
“Aspen Surgical distributors know that Aspen Surgical Bovie Smoke Shark II and Smoke Shark III offer powerful smoke evacuation performance for various sites of care with ULPA-grade particulate capture claims and remote activation options, ensuring the appropriate solution for a variety of procedures,” Aspen Surgical said.8
Surgical smoke is not only a staff safety issue; it can directly interfere with surgery. Significant amounts of smoke can impede a surgeon’s visibility during surgery, making precision difficult and potentially causing interruptions or delays. AORN’s guidelines link smoke to risks in minimally invasive procedures, such as decreased visibility and potential delays. They also raise patient concerns, noting that smoke byproducts like carbon monoxide and benzene can be absorbed.5
Smoke evacuation as compliance and standard-of-care
AORN’s guidelines stress the importance of smoke evacuation during all smoke-generating procedures. Key recommendations include placing capture devices near the source, using effective filters, showing clear policies and procedures, training staff, and measuring compliance. These elements – policy, training, equipment, and compliance – are essential for transitioning smoke evacuation from a “nice to have” to a “standard practice.”5
The Joint Commission’s Quick Safety emphasizes that organizations should follow Environment of Care guidelines to reduce risks from dangerous gases and vapors. It recommends establishing standard procedures, providing education, verifying staff competence, and using engineering controls to ensure consistent evacuation. While Quick Safety isn’t an official standard, it shows what surveyors expect to manage through their policies and risk management practices.2
OSHA doesn’t have a specific rule for smoke evacuation, but it does provide guidelines for managing smoke in surgical suites, like removing all smoke and ensuring proper capture distance. This lack of a single regulation, combined with acknowledgment of the dangers, has led to inconsistent practices. However, state laws are now accelerating the adoption of safety measures.1
State legislation is now a key factor for compliance. AORN reports that 20 states have passed laws on surgical smoke evacuation, with more states considering similar bills in 2026. This is important for distributor representatives because facilities in these states will require not just equipment but also policies, training, documentation and proof of compliance.6
1 Occupational Safety and Health Administration. Hazards of Smoke Generated from Surgical Procedures. U.S. Department of Labor;
April 18, 1996. Accessed March 3, 2026. www.osha.gov/laws-regs/standardinterpretations/1996-04-18
2 Joint Commission’s December 2020 “Quick Safety” PDF (Issue 56) on surgical smoke.
3 National Institute for Occupational Safety and Health (NIOSH). Control of Smoke From Laser/Electric Surgical Procedures. DHHS (NIOSH) Publication No. 96-128. Centers for Disease Control and Prevention. www.cdc.gov/niosh/docs/hazardcontrol/hc11.html. Accessed March 3, 2026.
4 Occupational Safety and Health Administration (OSHA). Hospitals eTool: Surgical Suite—Smoke Plume. United States Department of Labor. Accessed March 3, 2026. www.osha.gov/etools/hospitals/surgical-suite/smoke-plume
5 Association of periOperative Registered Nurses (AORN). Guideline Essentials: Surgical Smoke Safety—Key Takeaways. AORN, Inc. Published 2021. Accessed March 3, 2026. www.aorn.org/docs/default-source/guideline-essentials-documents/surgical-smoke-safety/keytakeaways_surgicalsmoke_2021.pdf
6 Association of periOperative Registered Nurses (AORN). Surgical Smoke-Free OR. AORN. Accessed March 4, 2026.
www.aorn.org/get-involved/government-affairs/policy-agenda/surgical-smoke-free-or
7 Jacobs LM Jr. Where there’s smoke: Quick Safety article recommends safety precautions. American College of Surgeons Bulletin. Published April 1, 2021. Accessed March 4, 2026. www.facs.org/for-medical-professionals/news-publications/news-and-articles/bulletin/2021/04/where-theres-smoke-quick-safety-article-recommends-safety-precautions/
8 Aspen Surgical. Bovie® Smoke Shark® III, 120V (SE03-120). Aspen Surgical. Accessed March 4, 2026.
www.aspensurgical.com/Product/SE03-120
How distributor reps can help facilities prepare for smoke evacuation protocols
- Evaluate the facility based on established guidelines. Check if there’s a written smoke policy, if smoke evacuation is used in all procedures that generate smoke, if capture positioning and activation practices align with OSHA/NIOSH guidelines, and if there’s regular compliance auditing. AORN offers templates and resources to help with implementation.5
- Support standard work and competency. Reps can reinforce practical setup details that decide real capture performance (e.g., keeping inlet close to the source; keeping the evacuator on when smoke is produced; using filtration configurations aligned with guidance and IFUs). When facilities treat this like other perioperative competencies, uptake improves.4
- Focus on choosing products that mitigate barriers and fit well into workflows. In outpatient and physician offices, space and portability are often limited. “Products like the Bovie® Smoke Shark III offer compact size, including accessories, and features designed for efficient workflows and compact spaces like physician offices, and ASCs,” Aspen Surgical said. 5
- To ensure readiness for future changes, facilities should have clear documentation. This should show: (a) a policy for evacuation during smoke-producing situations, (b) training records for staff, (c) proof of available and well-maintained equipment, and (d) results from compliance audits included in quality improvements. These practices align with AORN guidelines and Joint Commission safety recommendations.5