ASC Product Spotlight
By Pete Mercer
How evolving technologies are reshaping intubation in the ambulatory surgery center setting.
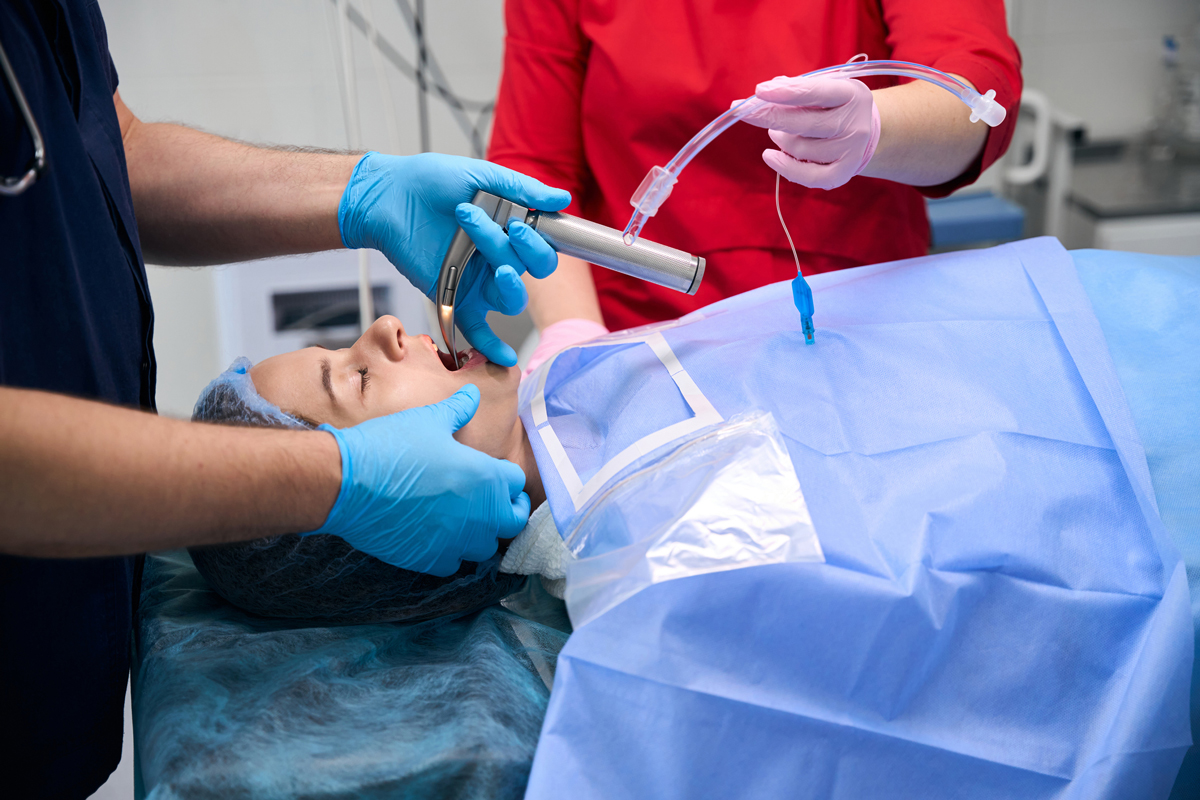
Endotracheal intubation is the cornerstone of airway management in ambulatory surgery centers, where precision, effectiveness and rapid recovery are tightly interconnected to the overall experience. Having a secure, definitive airway to facilitate ventilation and avoid aspiration is paramount to the safety of the patient. Without proper airway management, patients are at risk of injury or death during a procedure.
Repertoire Magazine spoke to Katie Bull, the senior global marketing program manager for Medtronic, about how complications from endotracheal intubation can impact patient outcomes in the ambulatory surgery center setting and how the TaperGuard™ cuff on Shiley™ endotracheal tubes addresses those complications.
Improving patient outcomes
The ambulatory surgery center setting is built for efficiency and versatility, creating a space for surgeons to perform procedures and send patients home all in the same day. To maintain such high standards of care and efficiency, surgeons need an endotracheal tube that reduces complications and side effects.
Endotracheal intubation is a critical part of the procedure, but it can create challenges for patient recovery. One adverse effect of endotracheal intubation, and the second most common healthcare acquired infection, is ventilator-associated pneumonia.
“There is an economic outcome of about an average of $40,000 for every new diagnosis of ventilator-associated pneumonia,” Bull said. “It is a higher risk for chronically ill patients, or those receiving ventilation over a longer period. Though this risk is likely lower in patients at ambulatory surgery centers, it is never zero.”
Because of the role that endotracheal intubation plays in an ambulatory surgery setting, it’s important that anesthesiologists have the best tools at their disposal for an effective and safe airway seal created by a cuff during surgery. Without that seal, patients experience complications and side effects like ventilator-associated pneumonia or poor oxygenation. However, if the cuff is not well designed and managed, it can cause complications, such as post-operative sore throat.
“One of the biggest complications that tends to negatively impact patient satisfaction is actually post-operative sore throat,” Bull said. “It might be minor when we think about sore throat, but it is a first sign of inflammation and injury. Not only does this affect patient safety and comfort, but it can also impact overall patient satisfaction scores, and that can impact the bottom line.”
Addressing post-operative sore throat
Post-operative sore throat is a common complication from intubation where the patient ends up with pain, discomfort and hoarseness in their throat after intubation and anesthesia. While a sore throat might seem like a minor inconvenience for someone in the ICU who is lucky to be alive, in surgery centers it’s an irritating and avoidable side effect of intubation. The culprit of post-operative sore throat is the endotracheal tube cuff that pushes up against the tracheal tissue during intubation.
The traditional endotracheal intubation cuff was created in the 1970s. They were designed as a high-volume, low-pressure cuff that expands to create a barrier in the airway so that fluids won’t drip down the esophagus during the procedure. That initial design hasn’t changed much over the years.
The challenge is that as the cuff expands to create a seal within the trachea and provide air to the lungs, the tubing can crinkle against high pressure points that come into contact with the tracheal tissue. Bull said, “That is what causes the inflammation and ultimately the sore throat. Even if the pressure is perfect, those wrinkles indicate a significant increase in pressure.”
With TaperGuard™ cuff technology, the designers at Medtronic were looking to create a “Goldilocks zone,” Bull said. “It is a little bigger on top and smaller at the bottom, which helps to create a sealing band when it’s fully expanded. One of the things we know is that through our design, we can decrease the amount of contact area. We’re able to decrease the amount of mucosal irritation and inflammation, which is what causes that post-operative sore throat.”
By removing these high-pressure points in the intubation process, ambulatory surgery centers can decrease the amount of post-operative sore throat for their patients, ultimately improving patient outcomes and patient satisfaction scores.
Improving ambulatory surgery center workflows
Due to the need for efficiency and results, surgeons and staff working in ambulatory surgery centers need reliable solutions for airway management. Tools like the TaperGuard™ cuff found on Shiley™ endotracheal tubes are designed to provide consistent airway management and to improve patient outcomes and physician workflows.
Bull said, “The ways in which people are using tools to intubate, including Shiley™ endotracheal tubes with TaperGuard™ cuff and the McGRATH™ MAC video laryngoscope have certainly changed the art of intubation and being able to do it more efficiently. Physicians can increase first pass intubation success using the McGRATH™ MAC video laryngoscope, which is very important.”
In fact, Bull said that the combination of TaperGuard™ cuff technology and the McGRATH™ MAC video laryngoscope can work in congress, in a “left-hand, right-hand” workflow. With the McGRATH™ MAC video laryngoscope in one hand and a Shiley™ endotracheal tube with TaperGuard™ cuff in the other, physicians can navigate airways with precision.
As for the future, Bull believes that things are only going to continue to get better in how they can improve the intubation process and develop further connectivity with their devices. “What kind of insights can the devices that we have in the body give clinicians in real time? Healthcare providers are really burnt out, and they have a lot going on. At Medtronic we have a commitment to service and a passion for innovation. We are continually seeing ways to improve patient care and the processes for the physicians and clinical teams.”